
Hospital acquired infections India conversations often jump straight to technology. That is the wrong order. Owners, medical directors, and quality heads first need a plain-English map of the problem: what counts as an HAI, how large the burden is, and why surfaces sit inside a controllable chain of transmission.
This article stays in epidemiology and operations—not product claims. It frames why environmental hygiene matters alongside hand hygiene, device care, and antimicrobial stewardship, so later technology decisions rest on the problem rather than the brochure.
For an honest account of what germicidal UV can and cannot add later in that chain, see UV-C disinfection limitations.
What Counts as an HAI
Health-care-associated infections (HAIs)—often called hospital-acquired infections in everyday hospital speech—are infections patients acquire in association with receiving care, not the condition that brought them in. Public-health agencies including the World Health Organization and CDC use surveillance definitions to keep counting consistent across facilities.
Four device- and procedure-linked types dominate many dashboards:
- SSI (surgical site infection) — infection at or near a surgical incision after an operation.
- CAUTI — urinary tract infection associated with an indwelling catheter.
- CLABSI — bloodstream infection associated with a central line.
- VAP — pneumonia associated with mechanical ventilation.
Those labels are not the whole story. Colonisation and infection with resistant organisms can also move through the shared environment—bed spaces, equipment, and the hands that touch both.
The Burden: Global Scale, Indian Context
WHO has long framed HAIs as a major patient-safety problem affecting hundreds of millions of patients worldwide each year, with higher prevalence often reported in low- and middle-income settings than in high-income ones. Exact facility rates vary by case mix, surveillance methods, and resources—so single “national average†headlines should be read with caution.
In India, hospital leadership already knows the qualitative picture: crowded wards, high device utilisation in tertiary centres, and a heavy presence of multi-drug-resistant organisms in many surveillance networks. ICMR and related AMR surveillance programmes have repeatedly highlighted resistant Gram-negatives and other priority pathogens in Indian healthcare settings; the operational implication is simple—every preventable acquisition matters more when treatment options are narrower. For why that stakes story elevates environmental hygiene year by year, see antimicrobial resistance environmental hygiene.
This post does not invent a precise India-wide prevalence percentage. It asks leaders to treat published WHO framing and local surveillance as directionally urgent, then to control what their own facility can control.

The Environmental Link
HAI surface transmission is not theoretical. Studies of prior room occupancy have repeatedly shown that when the previous patient carried certain pathogens, the next occupant’s acquisition risk rises—consistent with environmental contamination as one pathway among several.
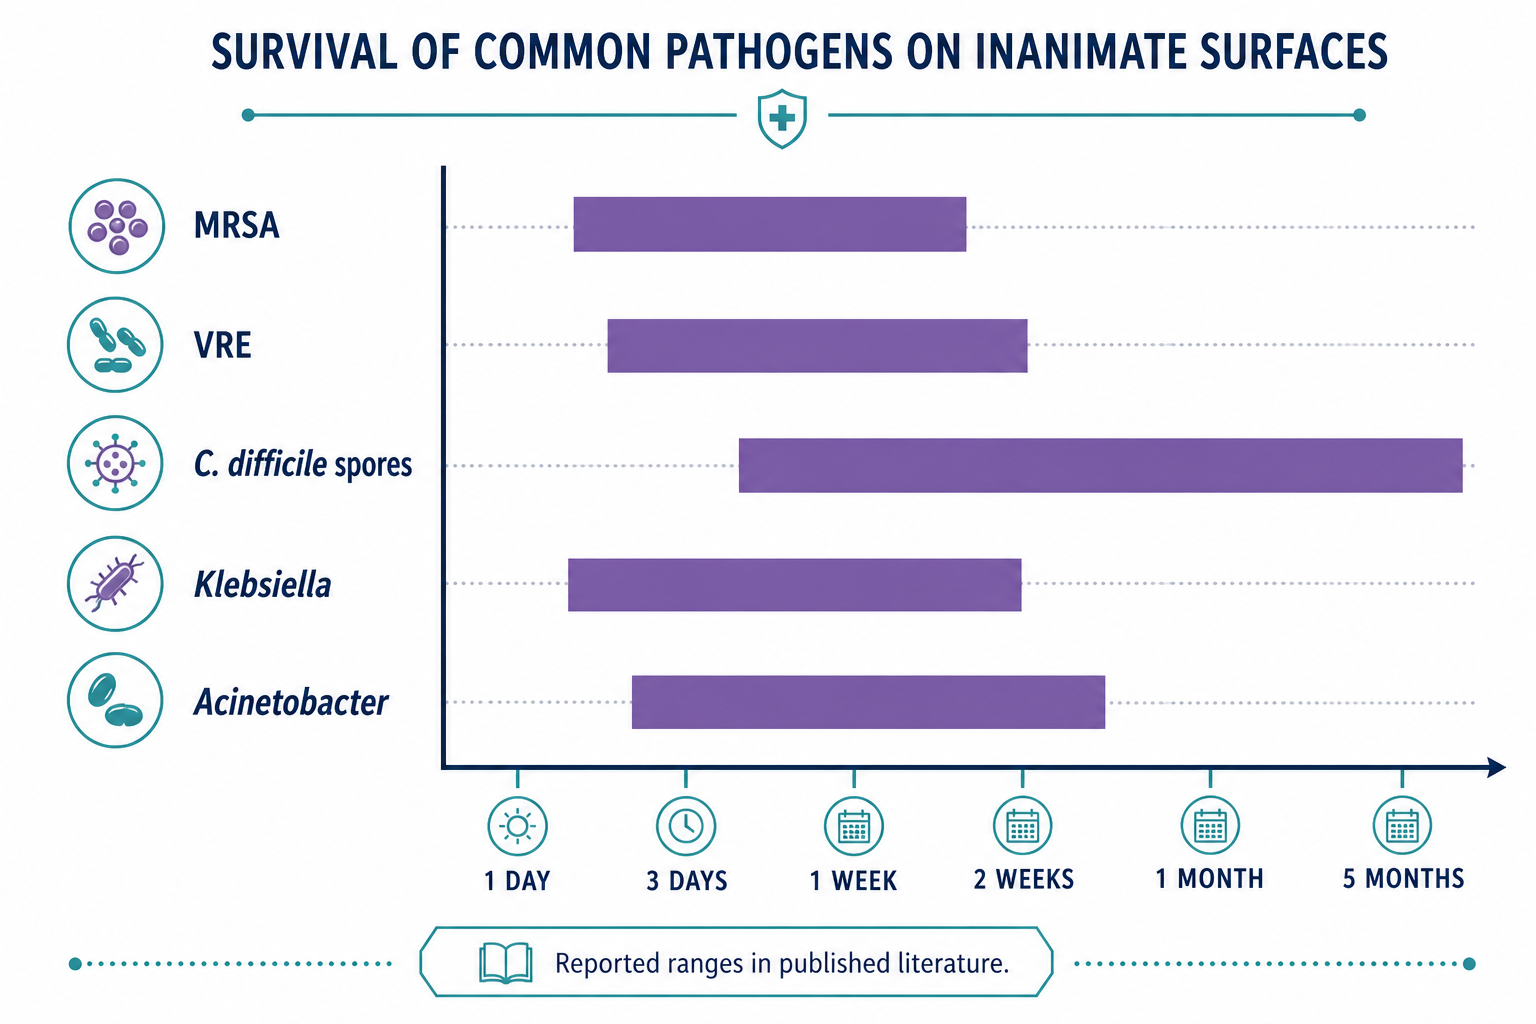
Key organisms persist on dry surfaces for meaningful periods. Published literature reports survival ranging from days to months depending on organism, inoculum, and conditions—including MRSA, VRE, Clostridioides difficile spores, Klebsiella, and Acinetobacter. Spores and some Gram-negatives are especially stubborn.
Hands remain the classic vector. Surfaces matter because they reload hands and equipment between patients. Break either link and you reduce risk; ignore surfaces and hand hygiene carries a heavier load than it should.
That patient → surface → hands → next patient loop is why terminal cleaning of vacated rooms, high-touch disinfection, and verification programmes sit inside infection-prevention architecture—not as housekeeping trivia.
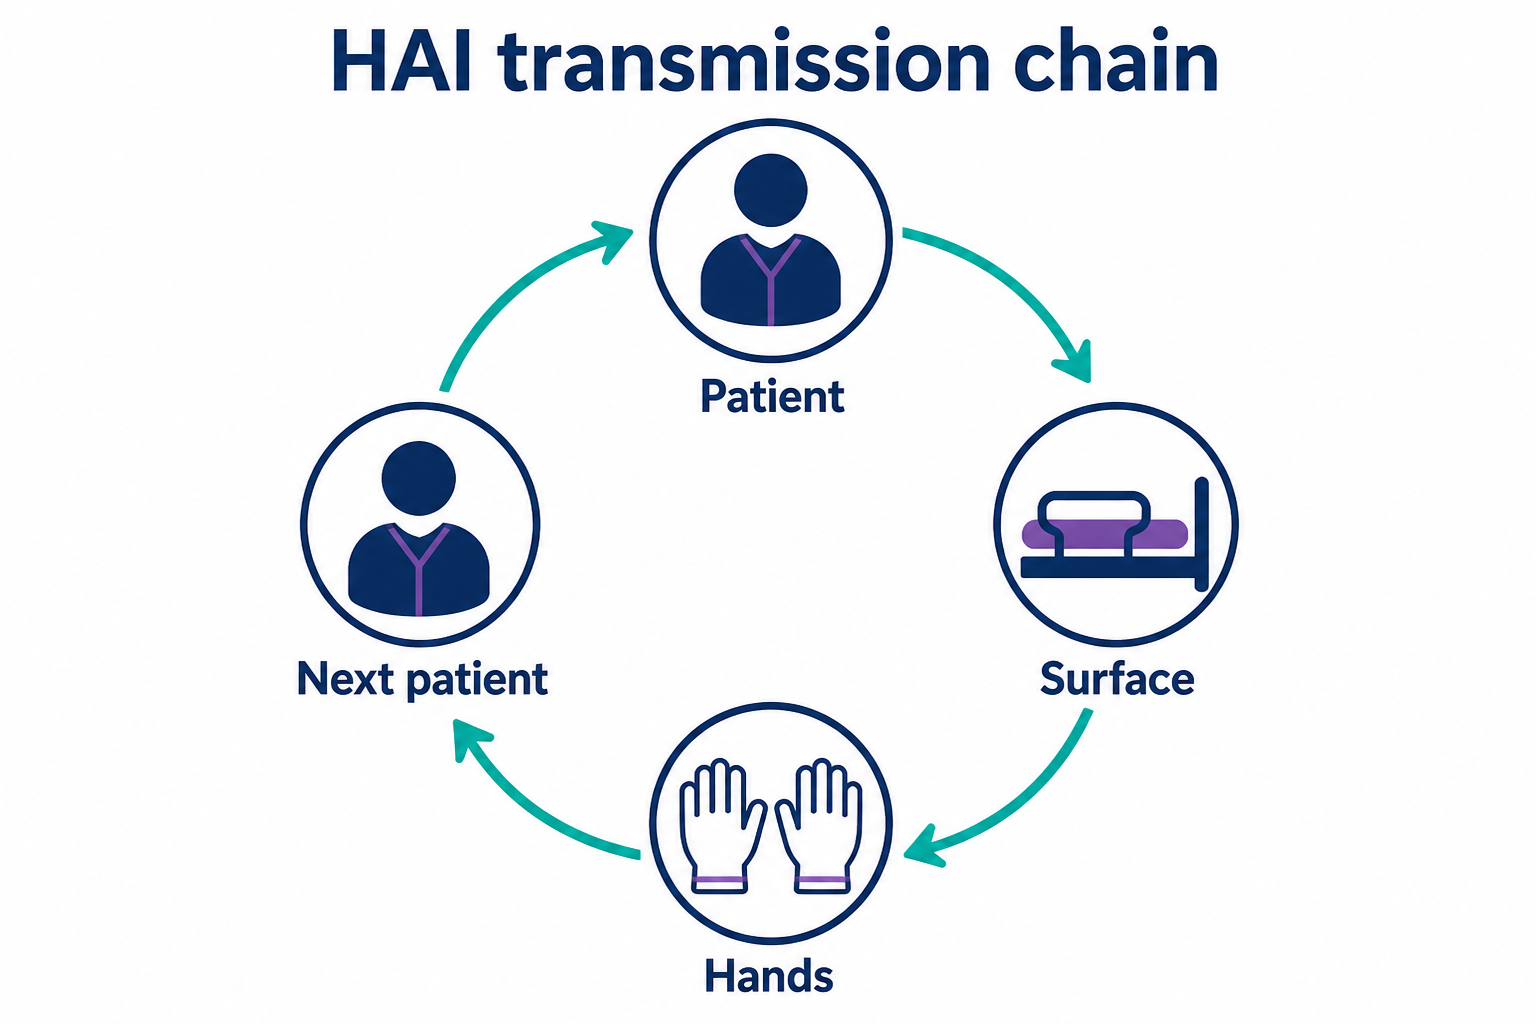
HAI Surface Transmission: Why the Environment Is Controllable
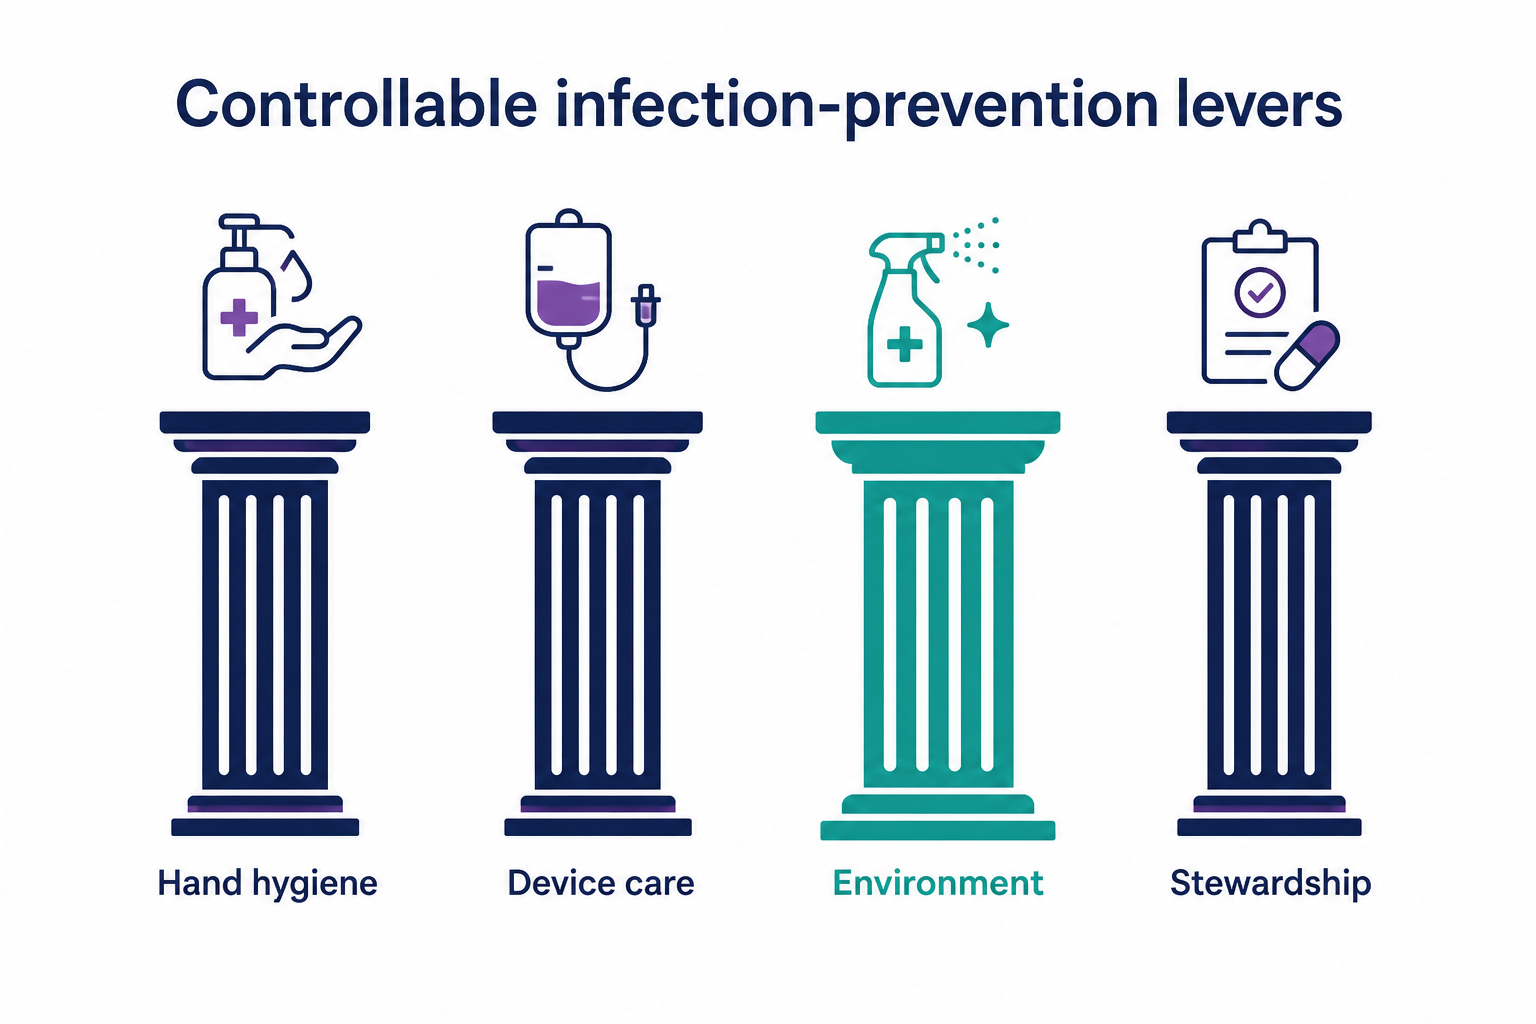
Antibiotic stewardship depends on prescribing culture across departments. Device-care protocols depend on nursing skill mix, product availability, and continuous training. Environmental hygiene—cleaning schedules, disinfectant choice, terminal processes, and verification—is more fully inside the facility’s operational ownership.
That does not make it easy. It makes it actionable. EVS leadership, IPC, and quality can define standards, measure compliance, and improve without waiting for a national formulary change. Surfaces are a controllable lever precisely because the hospital already runs the rooms.
For how optical blind spots complicate any no-touch adjunct later, see UV-C shadowed surfaces. For how intelligent UV programmes are discussed in hospital operations more broadly, see 10 Ways Intelligent UVC Disinfection Is Transforming Modern Hospitals.
The Cost Dimension
HAIs extend length of stay, raise treatment intensity, and consume scarce ICU and theatre capacity. Exact rupee figures vary wildly by specialty and payer mix—so this article keeps the cost case qualitative: every avoidable infection is an avoidable bed-day and an avoidable clinical risk.
For accredited and accreditation-track hospitals, environmental hygiene also carries documentation exposure. Assessors and surveyors ask whether cleaning and disinfection policies are implemented, monitored, and acted upon—not only whether a policy binder exists. Weak environmental records become survey friction even when clinical teams are excellent.
Investing in controllable surface processes is therefore both a patient-safety decision and a governance decision. It is not a substitute for stewardship or hand hygiene; it is the layer that keeps those programmes from fighting a contaminated room.
The honest caveat
Surface hygiene is one link in a multi-factor chain. Hand hygiene and device care matter as much. No single intervention—chemical, physical, or administrative—eliminates HAIs. Programmes that oversell one lever usually underperform on the others.
Key Takeaways
- HAIs are infections associated with care—not the patient’s admission diagnosis.
- WHO frames HAIs as a major global burden, often higher in many low- and middle-income settings.
- Prior-room occupancy and surface persistence link the environment to next-patient risk.
- Environmental hygiene is unusually controllable inside facility operations.
- Costs show up as LOS, treatment intensity, capacity loss, and accreditation exposure—without needing invented rupee headlines.
Frequently Asked Questions
Are hospital-acquired infections the same as health-care-associated infections?
In everyday hospital language they often overlap. Formal surveillance usually prefers “health-care-associated infection†(HAI) with specific case definitions from WHO/CDC-style frameworks.
Why focus on surfaces if hands matter most?
Hands are a primary vector. Surfaces matter because they contaminate hands and shared equipment between patients. Strengthening both links reduces risk more than arguing which is “most important.â€
Do pathogens really survive long on dry surfaces?
Published literature reports survival ranging from days to months for several priority organisms, depending on conditions. Treat those as reported ranges—not as a single number for every Indian ward.
Does better environmental hygiene replace antibiotic stewardship?
No. Stewardship, hand hygiene, device care, and environmental hygiene are complementary pillars. This article argues the environment is controllable—not that it is sufficient alone.
Where does SpotlessAI fit after this problem framing?
Only after the problem is clear. Spotbot Lite by SpotlessAI is discussed elsewhere as an adjunct to manual cleaning in vacated rooms—not as a cure for HAIs. Talk to our team if you want to explore how environmental processes fit your IPC programme after the fundamentals are in place.
Conclusion
Hospital acquired infections India debates should start with burden and pathways, not with gadgets. HAIs harm patients, consume capacity, and test governance—especially where resistant organisms narrow treatment options.
Surfaces are one controllable lever inside a multi-factor chain. Clean rooms, verify processes, and keep hand hygiene and device care equally visible. Technology, if used later, must respect that hierarchy.
If your facility wants a calm conversation about environmental disinfection as an adjunct—not a silver bullet—talk to the SpotlessAI team when the problem framing is already shared.
